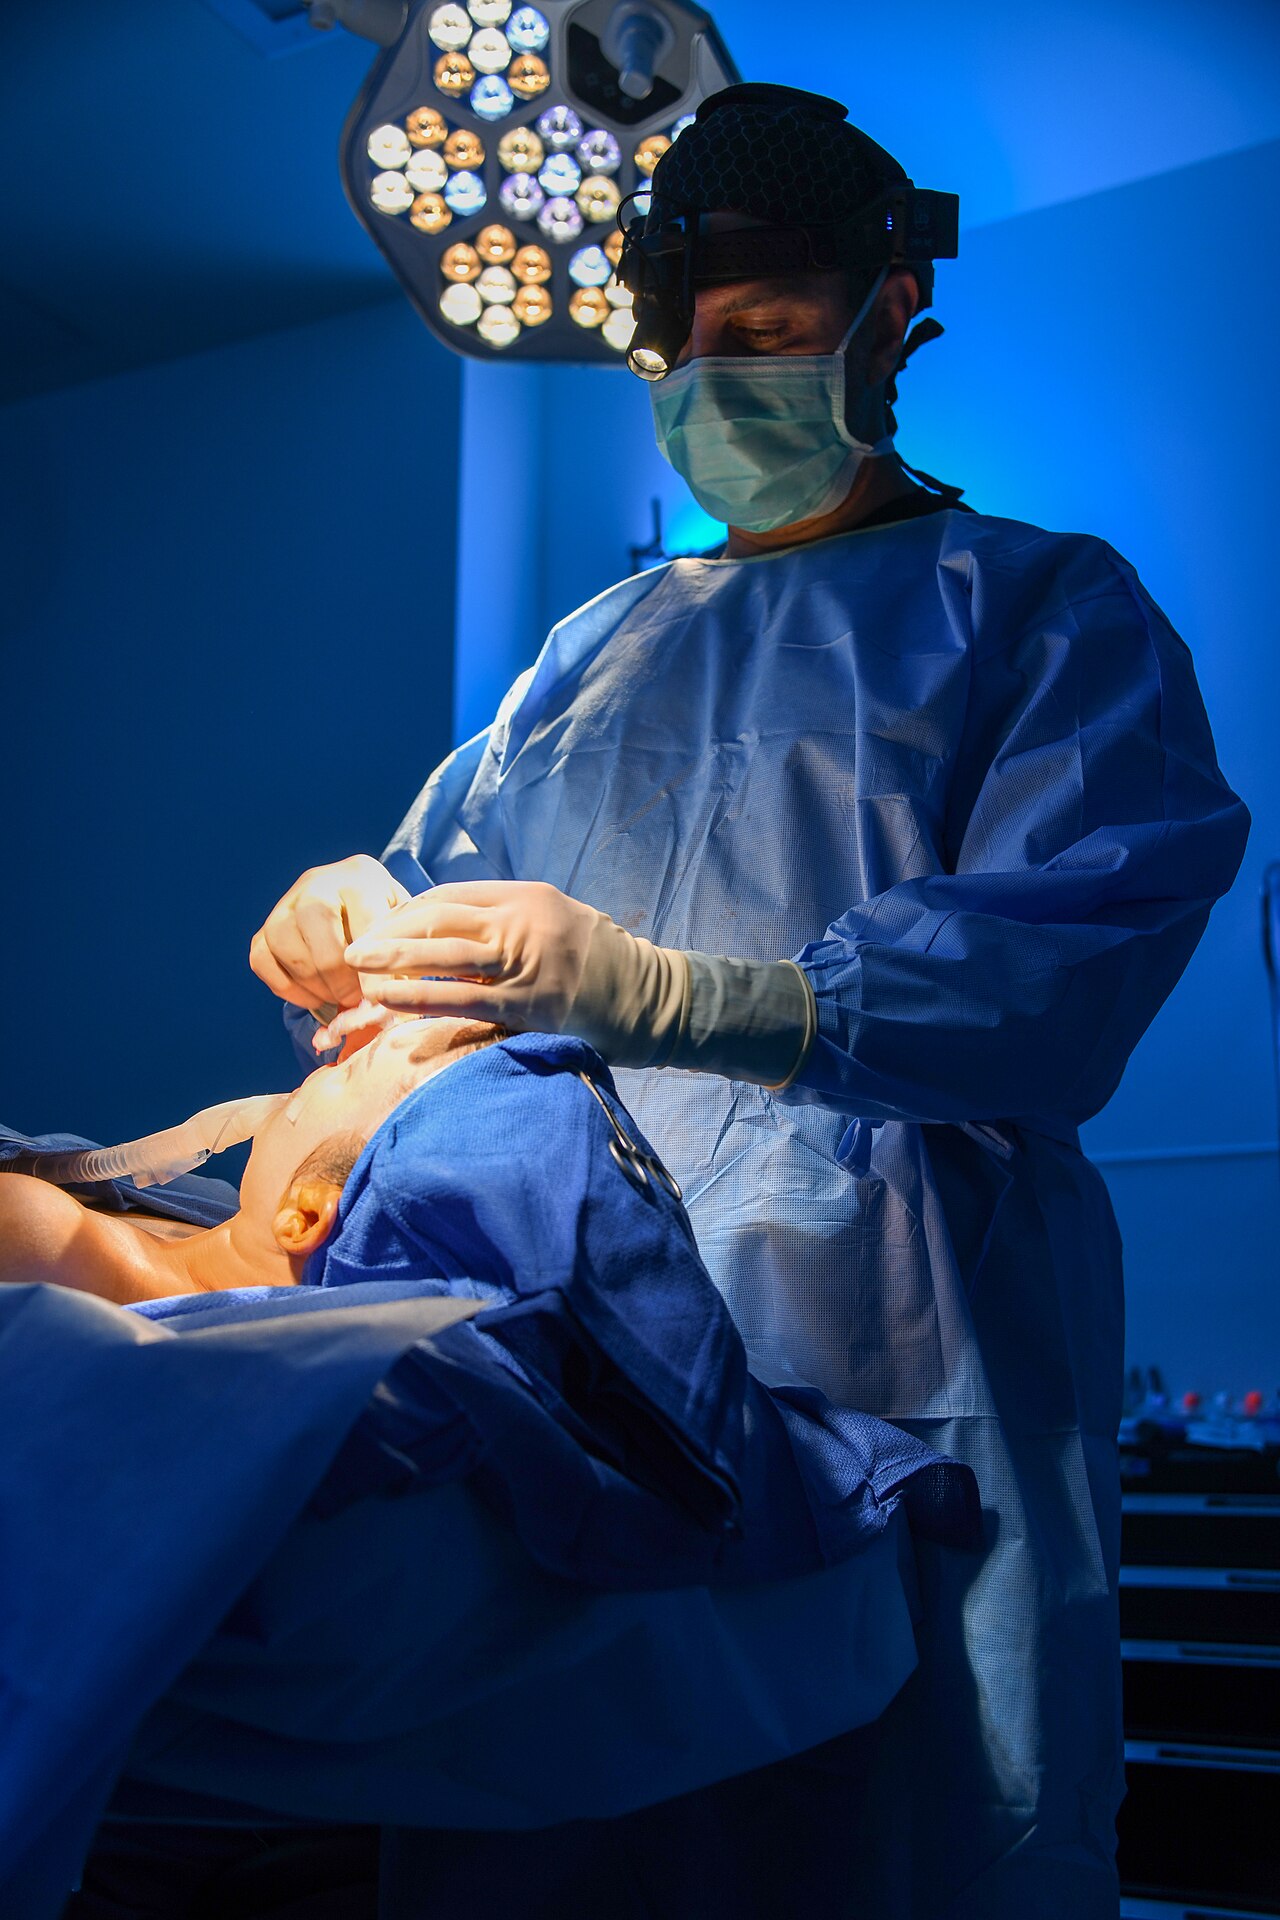

A routine operation is at the centre of an extraordinary legal claim. A mother of six is suing the doctors and hospital involved in her hysterectomy, alleging that complications from the surgery left her paralysed and led to the amputation of all four limbs. The case, now working its way through the courts, has drawn attention well beyond the legal filings because it compresses into one family’s story the fears every surgical patient carries into an operating theatre. Our health reporting sets out what is alleged, what is known, and what remains disputed.
The Claims at the Heart of the Case
According to the lawsuit, the patient underwent a hysterectomy — one of the most commonly performed major operations for women — and suffered severe complications in its aftermath. The filings allege that warning signs were missed or acted on too slowly, and that the cascade of harm that followed, including paralysis and the eventual loss of her limbs, was preventable with timely care. The defendants have denied wrongdoing, and the specific clinical sequence remains contested; as with all such cases, the allegations are claims to be tested in court, not findings.
What is not in dispute is the scale of the outcome. Losing all four limbs and mobility transforms every element of a life — work, independence, and the daily care of six children. Medical negligence cases of this severity are rare, and they are usually fought over a narrow question: not whether the outcome was terrible, but whether the care met the standard a competent team should have delivered at each decision point.
How Complications Can Cascade
Surgeons stress that hysterectomy is generally safe, but like all major surgery it carries recognised risks, including bleeding, infection and damage to surrounding structures. The danger in the worst cases is a cascade: an initial complication such as internal bleeding or sepsis triggers organ stress, circulation failure and tissue damage, and each stage narrows the window for rescue. Information from MedlinePlus on hysterectomy outlines the standard risks patients are counselled about before consenting.
Patient-safety research consistently identifies the hours after surgery as decisive. Escalation protocols — how quickly a deteriorating patient is reviewed, scanned, returned to theatre or moved to intensive care — are where outcomes are won and lost. Investigations in comparable cases typically examine charts minute by minute: what was observed, what was reported, and what was done.
The Questions the Case Raises for Hospitals
Whatever the verdict, cases like this force systemic questions. Were staffing and senior cover adequate when the patient deteriorated? Did the hospital’s early-warning scoring trigger the response it was designed to trigger? How was consent handled — not the signature on the form, but the conversation about rare catastrophic outcomes? Guidance from the American College of Obstetricians and Gynecologists sets expectations for counselling and post-operative surveillance that courts often use as reference points.
Hospitals also face the question of candour. Families in catastrophic cases frequently say that honest, early explanation would have changed their relationship with the institution, even when the medicine itself was defensible. Duty-of-candour rules in many jurisdictions now require exactly that openness.
What Happens Next
The legal process will be slow. Expert witnesses for both sides will reconstruct the operation and its aftermath, and the case may settle before any jury hears it. For the wider public following the story on our homepage, its significance is already clear: it is a reminder that surgical safety is built from unglamorous systems — monitoring, escalation, honesty — and that when those systems fail, the consequences are measured in a family’s whole future. The court’s task is to decide whether that is what happened here.